

Background
While the healthcare industry promises growth aplenty in the next 5 years, underutilisation remains a painful thorn in its side. Underutilisation – the failure to receive necessary medical care – is evident in a 43% underinsurance rate amongst working-age adults, 92% incompletion of high-priority preventive care services, and 9.2 million American adults not fulfilling their drug prescriptions. Naturally, much of the conversation is centered on the all-too-familiar C word (costs). This commentary comes at a timely point – just last summer, OBBBA introduced a slew of cuts to Medicaid and Affordable Care Act (ACA) subsidies, tightening the leash on eligibility, redetermination frequency, and premium tax credits. This effectively prices out almost 15 million Americans from health insurance, compounding the underutilisation issue.
At the same time, another $150 billion problem awaits. A supplementary perspective to the cost debate is that of non-attendance. Appointment no-show rates range between 5% to 30% across states, producing a cascade of worse disease management, poorer health outcomes, and greater medical cost burden. This is embedded in a framework of social determinants, institutional inadequacies, and behavioural science.
Not just a trip to the doctor’s
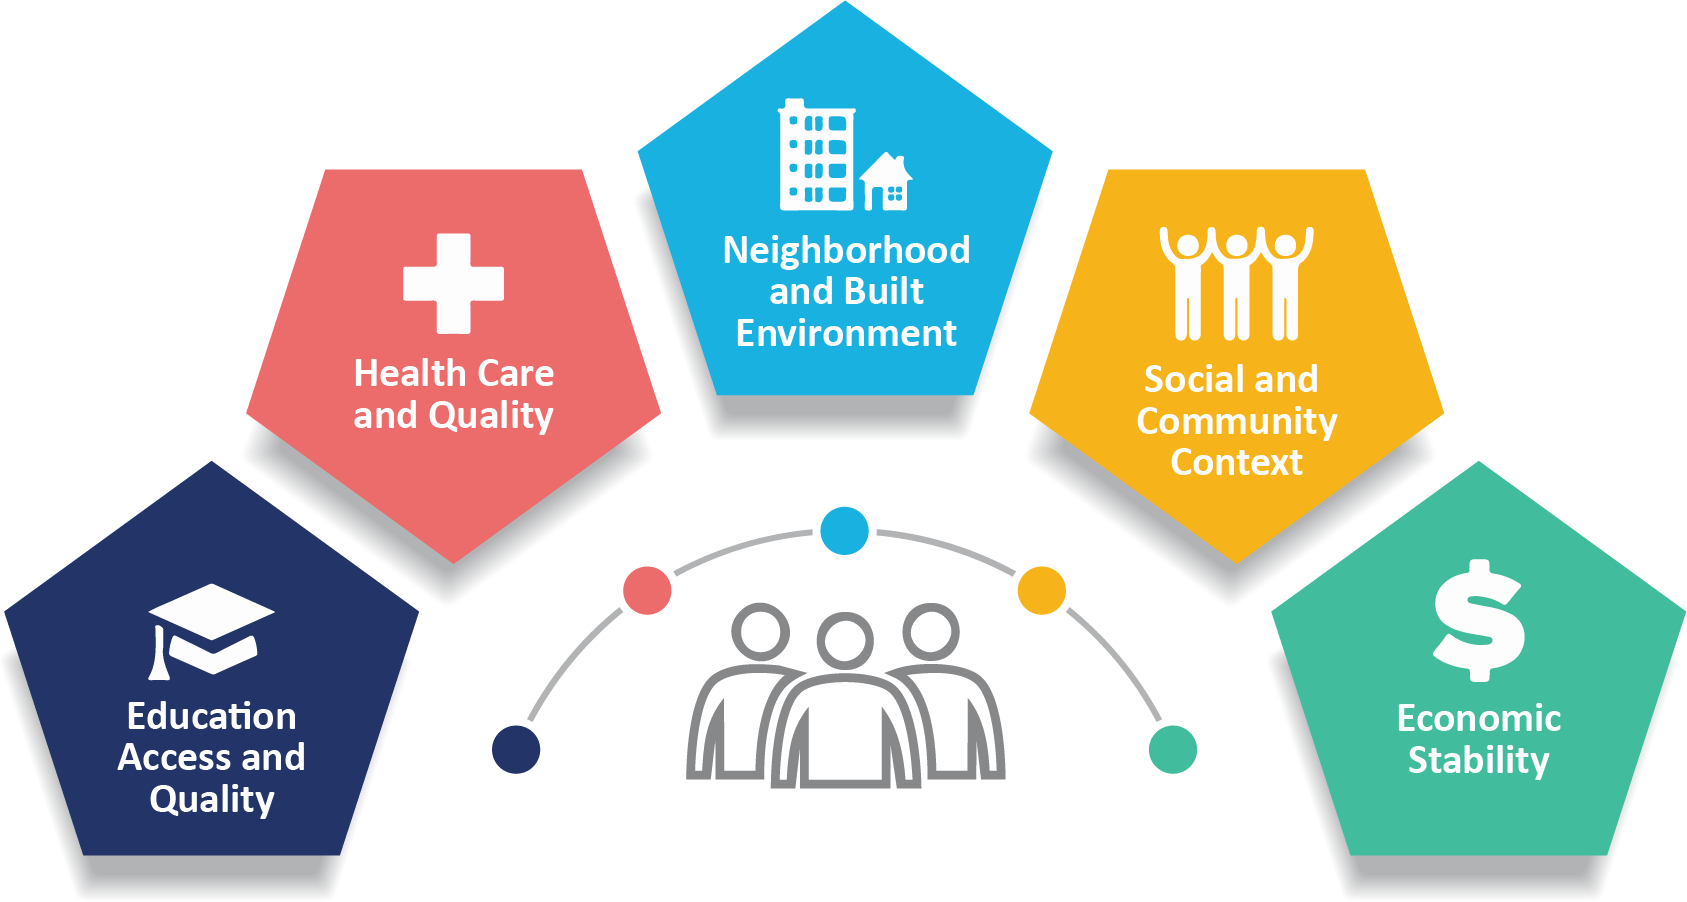
The phrase “social determinants of health (SDOH)” was first formalized by the World Health Organization in 2005, earlier championed by the distinguished epidemiologist Sir Michael Marmot. SDOH refers to the conditions in which people are born, grow, live, work, and age that contribute to the holistic health of an individual. A SDOH perspective on healthcare goes beyond purely medical determinants of health to add nuance on how structural forces beyond one’s control continually affect one’s care journey.
“If medicine is to fulfill her great task, then she must enter the political and social life. Do we not always find the diseases of the populace traceable to defects in society?” – Rudolf Virchow, German physician
Source: Centers for Disease Control and Prevention
Research consistently finds a suite of social determinants correlated with appointment non-attendance, with rates highest amongst patients with lower education levels. Beyond being possibly less informed about their health and the available healthcare touchpoints, less-educated patients also tend to have lower incomes, live in more rural areas, and grapple with more unpaid care work. A trip to the doctor’s entails significantly higher opportunity costs in terms of having to find a viable means of transport, longer travel time, costly parking, paying for a substitute childcare provider, lack of social and family support in attending recurring appointments, and a generally higher level of cognitive load and fatigue.
More comprehensively, the Area Deprivation Index (ADI) aggregates 17 measures of economic disadvantage across dimensions like education, income, employment, and housing quality, and serves as a proxy to understand how the neighbourhood environment affects one’s health. Higher scores on the ADI are strongly correlated with worse health outcomes, including higher risk of cardiovascular disease, premature ageing, and earlier death. When it comes to appointments, every unit increase in ADI is accompanied by a 11% increase in the odds of no-show. Furthermore, approximately ⅔ of no-shows live in neighbourhoods with the highest ADI.
Institutional inadequacies
A notable subset of SDOH is the institutional forces that shape the healthcare experience. Lengthy wait times and poor patient-physician relationships increase friction for patients in the care journey.
Wait times – which refer to the duration between the point at which the appointment is scheduled and when the appointment takes place – can influence patients’ illness progression. With wait times ranging from anywhere between 12 to 42 days across different specialties, patients may recover by themselves or have conditions worsen to the extent of seeking alternative treatments or passing on, especially amongst vulnerable groups like veterans.
To complicate things, a fragile patient-physician relationship may arise from a fragmented care journey, a lack of cultural sensitivity, and poor communication styles, sabotaging patients’ willingness to continue seeking care. A patient who sees a different provider each time with no longstanding and continuous understanding of their full medical history beyond the electronic health record, fails to offer culturally sensitive treatment plans, or pulls medical rank to silence questions, will only lose trust in the system. Each negative experience with a provider compounds negative expectation formation – disengagement today translates into non-attendance tomorrow. The national Culturally and Linguistically Appropriate Services (CLAS) standards are an important cornerstone of building stronger patient-physician relationships, but most of these standards fall short of being legal requirements.
A behavioral science perspective
Taking a step back from systems-level thinking to revisit the self, there are several behavioral science accounts for appointment non-attendance.
A potent barrier is our fallibility to present bias. Rooted in the concept of hyperbolic discounting, we discount the value of a future reward by a factor of the length of delay. In other words, the longer a patient has to wait for treatment and improved health, the more they devalue that outcome. Instead, they overweigh present circumstances, prioritizing convenience (both physical and mental). This is especially pertinent in the realm of preventive health, where the value of long-term health is even less perceptible if one experiences no immediate ailment. This bedevils the 92% health screening gap, and has contributed to 240,000 more hospital stays than needed in California.
More somberly, we struggle to confront the unknown. The looming fear of an abysmal diagnosis is what keeps 40% of Americans from attending their scheduled appointments. Popularized by Daniel Ellsberg, ambiguity aversion – the preference for choices with calculable risks over those with unknown, incalculable risks – compounds many patients’ anxiety towards medical authorities, medical procedures, and medical outcomes.
Alas, rather than overcoming the mental inertia and withstanding the mental turmoil, it is ostensibly much easier not to make the trip to the doctor’s.
A roadmap for LA County
With the U.S. disease burden ballooning, healthcare is much more than a national cost issue – it’s a deeply personal one that none can escape from or ignore.
As simple as it sounds, institutions can adopt automated multi-channel appointment reminders. Sending automated reminders 48 hours and 24 hours before the appointment can reduce no-shows by anywhere between 20-30%, while combining this with clinical staff telephone reminders can increase this to 50%. Moving beyond simple messages, these can incorporate predictive modelling of no-show behavior, personalized messages (using the patient’s name and citing the reason for the visit), or behavioral nudges (“not showing up will lead to X amount of administrative costs”).
The story does not end at the pre-appointment stage. Patients who drop out of the care pathway can be reintegrated through follow-up “We Missed You” messages to understand the reason for non-attendance and arrange for a new appointment date. More controversially, 42% of medical practices currently charge no-show fees. Among these practices, 25% of them reported improvements in no-show rates, while only 16% of practices without fees reported such improvements over time. Nonetheless, there is more to this modest improvement than meets the eye – punitive measures may actually increase cancellations (which are not tabulated under no-shows), discouraging attendance in fear of the possibility of not making the trip. Fees may fall disproportionately on vulnerable populations, while policies for waiving fees due to extenuating circumstances are not standardized across practices.
Critically, different measures target different symptoms of the greater malady. If no-shows result from forgetfulness, reminders and penalties pack a strong punch. If they are, however, the product of systemic frictions, the Sisyphean task of reforming care pathways takes center stage. The road ahead is lengthy and littered with challenges, but transparency, shared accountability, and equitable accommodations ought to guide the path forward.
References
McKinsey & Company. (2026). What to expect in US healthcare in 2026 and beyond. https://www.mckinsey.com/industries/healthcare/our-insights/what-to-expect-in-us-healthcare
Collins, S. R., Haynes, L. A., & Masitha, R. (2022). The state of U.S. health insurance in 2022: Findings from the Commonwealth Fund Biennial Health Insurance Survey. The Commonwealth Fund. https://www.commonwealthfund.org/publications/issue-briefs/2022/sep/state-us-health-insurance-2022-biennial-survey
Borsky, A., Zhan, C., Miller, T., Ngo-Metzger, Q., Bierman, A. S., & Meyers, D. (2018). Few Americans Receive All High-Priority, Appropriate Clinical Preventive Services. Health affairs (Project Hope), 37(6), 925–928. https://doi.org/10.1377/hlthaff.2017.1248
Centers for Disease Control and Prevention. (2023). Characteristics of Adults Aged 18–64 Who Did Not Take Medication as Prescribed to Reduce Costs: United States. https://www.cdc.gov/nchs/products/databriefs/db470.htm
TransLoc. (2024). The cost of missed medical appointments: A hidden burden on healthcare. https://transloc.com/blog/the-cost-of-missed-medical-appointments-a-hidden-burden-on-healthcare/
Alturbag M. (2024). Factors and Reasons Associated With Appointment Non-attendance in Hospitals: A Narrative Review. Cureus, 16(4), e58594. https://doi.org/10.7759/cureus.58594
McArthur, M., Tian, P., Kho, K. A., Bhavan, K. P., Balasubramanian, B. A., & Ganguly, A. P. (2024). Childcare as a social determinant of access to healthcare: a scoping review. Frontiers in public health, 12, 1443992. https://doi.org/10.3389/fpubh.2024.1443992
University of Wisconsin School of Medicine and Public Health. (n.d.). Neighborhood Atlas. https://www.neighborhoodatlas.medicine.wisc.edu/
Malloy, M., Tarima, S., Canales, B., Nelson, D., & Hanley, J. (2024). Identifying Risk Factors for Appointment No-Shows in a Pediatric Orthopaedic Surgery Clinic. Journal of the Pediatric Orthopaedic Society of North America, 5(3), 695. https://doi.org/10.55275/JPOSNA-2023-695
AMN Healthcare. (2025). 2025 Survey of Physician Appointment Wait Times and Medicare and Healthcare Technology Medicaid Acceptance Rates. https://online.flippingbook.com/view/83050962/
U.S. Department of Health and Human Services, Office of Minority Health. (n.d.). National standards for culturally and linguistically appropriate services (CLAS) in health and health care. https://thinkculturalhealth.hhs.gov/clas/standards
California Health Care Foundation. (2025). Not enough prevention in health care. https://www.chcf.org/resource/why-health-care-is-so-expensive/not-enough-prevention-in-health-care/
PatientPoint. (2023). PatientPoint patient confidence index. https://go.patientpoint.com/2023-patientpoint-patient-confidence-index
Aljuaid, M. A., Li, J., Lin, C., Sitwala, P., Daiker, D., Khorjekar, G., Gupta, A., & Tirada, N. (2023). Does the Combination of Phone, Email and Text-Based Reminders Improve No-show Rates for Patients in Breast Imaging? Current Problems in Diagnostic Radiology, 52(2), 125-129. https://doi.org/10.1067/j.cpradiol.2022.09.003